Tuesday, August 29, 2017

Ecstasy for PTSD: Some Background

You may have heard that the Food and Drug Administration has given the drug ecstasy (MDMA) its "breakthrough designation" for the treatment of PTSD. See this very thoughtful article in the Washington Post for details. 

I came out of blog-slumber to post about this because we're in the midst of planning an upcoming issue of TCPR (The Carlat Psychiatry Report) on PTSD, and because we've recently published a fair amount of material about MDMA. 

First, here's why we need better PTSD treatments. Only two drugs are FDA approved for PTSD: Paxil and Zoloft. Neither are very effective. In the original FDA trials, the drugs beat placebo but not by much; in fact, about 80% of the drug's efficacy is likely due to placebo factors. (See an older issue of TCPR for more on these trials). Various other drugs are used off label, such as Prazosin which helps with insomnia and nightmares, atypical antipsychotics, and alpha agonists such as clonidine and guanfacine. 

Psychotherapy is more effective than drugs, though the treatments most validated are imperfect and are variations of exposure therapy. Patients are asked to recount the trauma over and over again until they are desensitized to the anxiety elicited by the memory. The problem is that this process is emotionally painful and many patients just can't bear the idea of having to recall their trauma (such as a rape, a military attack, or a natural catastrophe) repetitively. 

Enter MDMA. Last March we published an issue of CATR (The Carlat Addiction Treatment Report) on psychiatric uses of street drugs. Psychiatrist Philip Wolfson wrote an overview of the many therapeutic uses of hallucinogens and other substances (full article here), and we interviewed the training project manager of the MDMA/PTSD research program, Shannon Clare Petitt (full interview here). I've reproduced a portion of Petitt's interview at the end of my post below. These are clearly boom times for those seeking creative ways to repurpose "recreational" drugs for healing purposes. In my opinion, that's a good thing for psychiatry, as we have been in something of a pharmacological rut for many years now. 

Excerpt from "MDMA-Assisted Psychotherapy for Posttraumatic Stress Disorder", an interview with Shannon Clare Petitt, MA, first published in The Carlat Addiction Treatment Report, Vol 5, No. 2, March/April 2017. Ms. Petitt is the MDMA therapy training program manager at MAPS Public Benefit Corporation (MPBC), Santa Cruz, CA.
CATR: You work for MPBC, MAPS Public Benefit Corporation, a subsidiary of the Multidisciplinary Association for Psychedelic Studies, as MDMA therapy training program manager. What does your work involve?
S. Petitt: My work is focused on managing the program that selects and trains researchers for the MDMA-assisted psychotherapy protocols MPBC is conducting. As you might imagine, it’s important to select applicants who have experience working with trauma and are truly well suited for MDMA-assisted psychotherapy. Over the past year, we have reviewed 300 applicants, and right now we are in the midst of training 80 people who will work on therapy teams for Phase 3 trials. In addition to the training program, I also served as co-therapist on the MAPS-sponsored Phase 2 trial of MDMA-assisted psychotherapy for anxiety associated with life-threatening illness.
CATR: Most people know MDMA as “ecstasy,” a drug of abuse. How does it assist in psychotherapy?
S. Petitt: We have two main hypotheses that drive our research. The first is that MDMA reduces activity in the amygdala, which is the fear center of the brain. This is supported by animal research showing MDMA facilitates fear extinction learning. This is important because the hallmark of PTSD is reexperiencing—feeling as though the traumatic experience that happened in the past is actually happening in the present moment. MDMA allows people to recall traumatic memories without the same fear response, and of course this makes it much easier to process and recontextualize those memories.
CATR: It sounds like MDMA helps make recalling traumatic memories less aversive. What’s the second hypothesis?
S. Petitt: It’s relational. Working with trauma is about establishing trust and safety, and MDMA facilitates that.
CATR: In what way?
S. Petitt: MDMA is not a classic psychedelic that induces hallucinations or distortions. It’s better described as an empathogen, or some people call it an entactogen, because it produces feelings of compassion for oneself and others and helps establish trust. It’s so effective in this area that it was actually used in couples therapy before it became illegal in the U.S.

Friday, February 17, 2017

Antidepressant News: Just the Right Amount of Opiate?

In the early 1950s, opium was considered an effective treatment for depression, but gradually it fell out of favor as its addiction risk became clear. Nonetheless, there's no denying that opioids rapidly elevate the mood of just about anybody, even the very depressed. So that's a pretty tantalizing challenge: Is it possible to harness the elating effects of opiates while avoiding the addictive "side effects," as it were.

source: amrismartsourcing.com
A recent contender is a drug made by Alkermes code named ALKS 5461. This drug is a combination of buprenorphine and samidorphan. Buprenorphine is an opioid which is often combined with naltrexone to produce drugs for opioid use disorder, such as Suboxone. Samidorphan is a derivative of naltrexone, and it doesn't antagonize opioid receptors quite as avidly as its cousin. So combining these two might just allow enough opioid receptor stimulation to squeeze through to treat depression, without it being too appealing to potential addicts.

Early phase I and phase II clinical trials with small numbers of subjects were promising. Based on these results, the company conducted larger phase III trials, called the FORWARD (Focused On Results With A Rethinking of Depression) trials. Unfortunately, the first two of the larger trials failed, showing no improvement over placebo. The third trial (FORWARD-5) was more successful. In that trial, 407 patients with depression unresponsive to a trial of standard antidepressants were randomized to receive ALKS 5461 as an adjunct, or placebo as an adjunct. The company reports that patients receiving the higher dose of 2mg of ALKS 5461 did significantly better than placebo, as measured by the MADRS rating scale. Side effects were nausea, dizziness, and fatigue.

Will this drug see the light of day? It’s unclear, but according to pharmaceutical industry news sources, Alkermes has been talking up its latest results with the FDA and hopes to get approval at some point within a year or two. It sure would be nice to have another antidepressant at our disposal.

Wednesday, September 7, 2016

Have Companies Stopped Ghostwriting? BMJ Article Says "No"

A new article in the British Medical Journal (BMJ) by Alastair Matheson takes a fresh look at ghostwriting in medical research. Apparently, pharmaceutical companies are waging a campaign to convince us that they are now opposed to ghostwriting. But Matheson argues that the practice continues, only under a different name: "editorial assistance."

It comes down to how we define ghostwriting. The standard definition in the Oxford dictionary is straightforward: a ghostwriter is “a person whose job it is to write material for someone else who is the named author."

If a company recruits academics to put their names on a paper, but then pays an unnamed medical writer to actually compose the paper, that's clearly ghostwriting and is a deceptive practice. But it's rarely so straightforward. Yes, companies recruit academics to help design, conduct, and write research studies. Yes, companies also hire medical writers to do the grunt work of writing up the results of a study. Typically, medical writers are acknowledged in small print in the footnotes. Companies are claiming that this acknowledgment means they are being honest, and properly informing readers that these non-academics also contributed to the paper. Therefore, they are innocent of ghostwriting.

Matheson disagrees, arguing that these medical writers do a lot more than just the tedious rendering of the methods and results of research. Instead, they work closely with the funding companies to shape the manuscript in such a way that the funded drug looks good. The identified authors, whose names are in lights just below the title, may indeed edit and review the paper before publication, but the companies have plenty of leverage over the final content.

Simply publishing a footnoted acknowledgment of a medical writer for "editorial assistance" is not enough, he says, because it covers up a process in which the company uses the medical writer as a conduit to spin the paper in a commercial way. The solution? The International Committee of Medical Journal Editors (ICMJE) should require that any writer who contributes to the manuscript should be listed as an official author. He points out that the journal Neurology already has this policy in place, and indeed, if you look up their authorship policy here, you'll find the following crystal clear statement:

"Professional writers employed by pharmaceutical companies or other academic, governmental, or commercial entities who have drafted or revised the intellectual content of the paper must be included as authors."

Furthermore, Matheson calls for ICMJE to develop other rules to prevent what he calls "attributional spin." For example, in deciding the order of the listed authors, those with the most actual influence over content (often the employees of the company) should be listed first, rather than being listed after the academics as is sometimes done.

It's a good read. The article piqued my curiosity because over the last few days I've been slogging through the literature on antidepressant-induced sexual dysfunction to write an article for the next issue of the Carlat Psychiatry Report. Most of the articles are industry funded, and all of them relegate mention of medical writers to footnotes.

For example, here's page 1 of one of the studies I've read. There are five authors, the first of whom is an independent academic, and the last four are employees of vilazodone's maker Forest.


And here's the last page of the paper, which acknowledges Adam Ruth, a medical writer, for "writing assistance and editorial support."


According to Matheson, Adam Ruth should be listed as an author. I agree.

It's true that in this particular case, you could argue that Forest is already being transparent enough by clearly stating that four of  the authors are company employees. Nonetheless, adding the medical writer as an author reminds the reader that industry funded articles are essentially commercial, rather than academic enterprises. Maybe that's obvious, but sometimes it's worth stating the obvious.


Monday, October 5, 2015

Boston Globe Article about Genetic Testing in Psychiatry


It would be fantastic to have a lab test to help us decide which drugs to prescribe in psychiatry. See Sunday's great Boston Globe article that picked up on our recent coverage of the GeneSight test. 


It's a promising technology, but the marketing has leap-frogged ahead of the science. 

This Wednesday afternoon I will be participating in a webcast with journalists and other doctors about this controversial issue. 

The chat will begin this Wednesday, 10/7, from 3:30 p.m. to 4:30 p.m. The conversation will appear in the embed below and on the New England Center for Investigative reporting page here. You can start submitting questions now though.

Live Blog What should you know about psychiatric genetic testing?

Wednesday, September 16, 2015

The TMS Wars: Psychiatry Goes High Tech

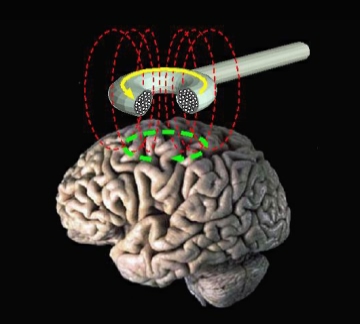
In the pages of The Carlat Psychiatry Report, we’ve covered transcranial magnetic stimulation (TMS) numerous times—most recently in the current issue. For those who haven’t heard of these devices, they work by pulsing magnetic fields into the brain. The magnetic fields stimulate neurons—far more gently than electroconvulsive therapy. The theory is that this gentle brain stimulation, focused on specific brain regions, eases depression.

After skeptically covering this technology for almost a decade, I’m finally convinced that it actually works.  A recent systematic review, funded by the U.S. Government and written by authors with no ties to any TMS company, endorsed the technology pretty strongly. They found that for patients who were treatment resistant (those who had not responded to at least two antidepressants), TMS was three times as effective as the sham (placebo) control group.

Admittedly, it’s a little creepy and science-fictiony that we are in an era when magnetic stimulators are actually effective for changing our moods. But so be it.

Now that we have an effective device in psychiatry, it’s kind of fun to see these manufacturers competing for market share. There are already two TMS devices on the market: NeuroStar and Brainsway.

Over the past couple of months, two new companies have jumped into the fray. I received this letter from a company called Magstim, announcing their new Rapid 2 Therapy System. Without going into too many technical details, this device, as you can see below, looks like a glorified dental chair with a sleek brain stimulator attached.

Magstim

MagVita
MagVita is an even newer device, just approved last month.

As is turns out, these two upstarts are threatening to shake the nascent TMS industry to its core. Why? Because they are entering the market with an offer that’s almost impossible to refuse: no per-use fee. Both Neurostar and Brainsway charge a bundle of money up front to buy or lease the device, then they charge an extra $100 or so per treatment for disposable “shields” which aren’t actually necessary. They are simply income generators.

Magstim and MagVita are chucking those shields—saving doctors thousands of dollars in pointless charges.

What does this mean for patients? Probably that the treatments will be more affordable—more insurers will cover the cheaper Magstim and MagVita devices, and patients who must pay out of pocket will have less sticker shock. And what does this mean for Neurostar and Brainsway? Lots of anxiety, and deep discounts to try to keep up with Magstim and MagVita.


Want to learn more about neurostimulation devices? 
The July/August issue on “Interventional Psychiatry” offers an overview of this fast-changing world and is available as an individual purchase which includes 2 category 1 CME credits.
  • Summary of neurostimulation methods, including: transcranial magnetic stimulation (TMS), magnetic seizure therapy (MST), vagus nerve stimulation (VNS), transcutaneous vagal nerve stimulation (tVNS), transcranial direct current stimulation (tDCS).
  • Expert Q&A on the past and future of TMS with Dr. Mark George of the Brain Stimulation Laboratory at the Medical University of South Carolina.
  • Expert Q&A on what it means to be an "interventional psychiatrist" with Dr. Nolan Williams of Stanford University.
  • Review of the Fisher Wallace and Alpha-Stim devices as treatment options for depression.
  • A practical guide on which TMS device you should buy (if any) for your practice.

Thursday, August 20, 2015

Flibanserin: 5 Things to Consider Before Passing Judgment on the “Female Viagra”


Flibanserin (brand name Addyi) has just received a controversial and complicated FDA approval for the treatment of low sex drive in women. There’s a lot of outrage in the blogosphere, much of it centered on the lobbying of the FDA by disease advocacy groups.  I agree that this politicization of what should be a scientific process is embarrassing to both Sprout and its supporters. Nonetheless, I'm not nearly as hard on flibanserin as some of my colleagues.

Here’s why.

1. Hypoactive Sexual Desire Disorder is as real as any other source of distress, and deserves treatment.
 
Sure, I get that when it comes to subjective problems, it’s easy to stretch the definition of what constitutes a disease. But who are we to judge whether an affliction is severe enough to merit treatment? An example is social anxiety disorder. Some call it the medicalization of shyness. But if you’ve ever treated someone with this problem, you know that extreme shyness can limit your potential for a normal, happy life.

Low sexual desire may not be a public health emergency, but it’s a real problem for about 10% of women.  If they want to take a pill to make their lives a little better, why not? We allow Botox for wrinkled eyebrows, Rogaine for hair loss, Provigil for jet lag. Why not a drug for low sexual desire?

2. Flibanserin is a female Viagra—just a much less effective version. 

Lots of bloggers are saying that Flibanserin is no female Viagra. I don’t buy it. Trivially, yes, they are different drugs because they have different mechanisms of action. Viagra and the rest of the PDE-5 inhibitors enhance erection by shunting more blood to the vessels of the penis. Addyi’s specific mechanism isn’t known, but the drug is a serotonin 1A receptor agonist and a serotonin 2A receptor antagonist and enhances sex via greater desire. But the purpose of both drugs is the same—they are supposed to improve peoples' sex lives. Whether they do it via blood flow or serotonin doesn’t really matter.

However, there is one huge difference between Viagra and Addyi—namely, Viagra is extraordinarily more effective than flibanserin. Studies of Viagra and other PDE-5 inhibitors have found that around 80% of men on the active drug report erectile improvements vs. 20-30% of men taking placebo. That means that 50-60% of men gain benefit over and above placebo. Flibanserin? The FDA’s analysis of the data concluded that 8-13% of women had some desire benefit beyond the effects of placebo. If Viagra is a Starbuck’s triple espresso, flibanserin is a Dixie cup of cafeteria coffee.

3. Flibanserin causes side effects. In addition, water is wet. 

Come on, the nature of all medical treatment is a balance between benefits and side effects. Antipsychotics cause weight gain, antidepressants cause impotence, Viagra causes lightheadedness and low blood pressure especially if combined with nitrates. Flibanserin causes side effects too, such as sedation, dizziness, and low blood pressure.

There’s also an interaction with alcohol but we don’t know how dangerous it is. The company did a study of 25 people (most of whom, oddly enough, were men), and found that one person fainted when combining flibanserin with a moderate amount of alcohol. Five people got dizzy on the combination, but three people also got dizzy in the alcohol plus placebo group, and 4 got dizzy with flibanserin alone. (For the results of the Alcohol Study, see page 77 of this PDF report.)

So it’s not clear from these data how concerned we should be. Certainly, Sprout needs to do more studies. An alcohol contraindication is reasonable. Do we really need to limit flibanserin scripts to certified prescribers? Do we really need a REMS, and the requirements for CME that will inevitably be funded by the manufacturer? It sounds like a case of FDA over-reaction to me. I’ve been prescribing MAOI antidepressants (another "dangerous" drug) to patients for years. There’s a long list of foods they can’t eat and meds they can’t use. Our discussion of side effects is part of a standard medical visit. I don’t need a special certification to talk to my patients about these things.


4. Flibanserin will, indeed, be prescribed off-label, just like virtually every other FDA-approved medication. 

The FDA indication for flibanserin is highly restricted. It’s indicated only if there is low sexual desire without any clear cause. Thus, if the patient is depressed or anxious, and you think that may be contributing toward the low desire, it’s off-label. If there’s a medical condition, like cancer, causing the problem, it’s off-label. It's undoubtedly true that in the real world, doctors are going to be prescribing the drug for these off-label populations and many more. That’s no different from most other meds we prescribe. In psychiatry, for example, almost all the medications we prescribe for children are off-label, because there are so few meds with FDA approval.

5. Adriane Fugh Berman said it best as quoted by the New York Times: Flibanserin is a “mediocre aphrodisiac with scary side effects.”
 
But often in medicine, that’s exactly what we have to work with: mildly effective medications with side effects. Flibanserin may be mediocre, but it’s not ineffective. I look forward to cautiously prescribing it to those women in my practice who might benefit from it. Time will tell whether it becomes popular. If it’s as mediocre as the data suggests, patients won’t refill their prescriptions—in which case the market will quietly close the door on the little pink pill.


Wednesday, August 5, 2015

Vyvanse: Is History Repeating Itself?

One of the benefits of having the Carlat World Headquarters here in beautiful Newburyport, Massachusetts is that we get to work next door to an iconic antiques barn called Oldies. It's a wonderful stockpile of odds and ends that range from decommissioned lobster traps to faded movie posters.


The other day I came across an old issue of LIFE Magazine with a cover story on “The Dangerous Diet Pills: How Millions of Women are Risking their Health with Fat Doctors.” The date? January 26, 1968, which was smack dab in the middle of the amphetamine epidemic that prompted Congress to pass the bill creating our current system of scheduled, and controlled medications.


What, if anything, does this issue of LIFE teach us about the potential dangers of Vyvanse’s recent approval for binged eating disorder? This “exclusive report” was based on investigative journalist Susan McBee’s undercover visits to 10 “fat doctors.” She was given cursory exams and, although she was not overweight (5’5”, 125 pounds), virtually every physician prescribed her various pills, including amphetamines, barbituates, sex hormones, and diuretics. One office insisted she pay cash--no personal checks--in order to receive the pills.

How is this nearly 50-year-old article relevant to the age of Vyvanse? This was a story of unscrupulous doctors running pill mills for women who wanted to lose weight. The diagnostic process--if there was one--was sloppy and all-inclusive. If you came to one of these doctors requesting amphetamine, you were assured of getting a script, regardless of your diagnosis.

As a recent New York Times article shows, history is repeating itself. The Affordable Care Act has a provision requiring coverage of obesity treatment, and doctors are taking advantage of this by opening chains of lucrative weight loss clinics. Some are selling medications directly to patients, such as phentermine, which, like Vyvanse, is an stimulant.

It seems only a matter a time before Vyvanse pops up in the menu of options for patients being seen by the new breed of diet doctors.

Don't get me wrong--Vyvanse is effective for binge eating disorder, as we discussed in our recent CME article (subscribers to The Carlat Psychiatry Report can read it here).

If a patient came to me and said, “Doctor, I’ve heard about Vyvanse for binge eating, and I’d like to try it,” I would carefully ask about their eating habits in order to establish an actual pattern of binge eating. But what if the patient was more of a grazer than a binger? What if I sensed that the patient was simply looking for a weight loss drug and had no binge eating problem at all? I wouldn't prescribe a drug that has a high risk of abuse and diversion.

As was true in 1968, doctors are free to prescribe meds for indications not approved by the FDA. I predict that many women (and men) will be asking for Vyvanse to lose weight, and will walk away with the prescription, whether or not they have BED.

It's been nearly a half century since the LIFE article, and we're still prescribing speed for weight loss Let’s not let it get out of hand.